Clinical Case Review A de-identified review of delayed spinal rod migration toward the thoracic cavity, with attention to imaging, possible failure mechanisms, revision planning, follow-up and the limits of what can be concluded from a single reported case.
Publication and authorization notice
Written informed consent for publication and permission to use the de-identified images were obtained and are retained by the publisher. Direct patient, surgeon and hospital identifiers have been removed from this web version.
Case summary
According to the case materials supplied for review, a middle-aged adult with a remote history of posterior thoracolumbar fusion developed progressive pleuritic chest discomfort and exertional dyspnea. Radiography and computed tomography reportedly demonstrated cephalad migration of a longitudinal spinal rod toward the left thoracic cavity after disengagement from the posterior construct.
The reported management involved removal of the migrated rod and revision of the posterior fixation in a single operative session. No general claim about the superiority of a device, thread form, cross-link configuration or surgical approach can be made from this case alone.
Spinal rod migration is an uncommon but potentially serious delayed complication of spinal instrumentation. Published case reports describe migration into the spinal canal, retroperitoneum, pelvis, mediastinum and thoracic structures. The mechanism and appropriate management vary substantially between cases, which is why imaging, fusion status, bone quality, construct condition and proximity to vital structures must be evaluated individually.
Evidence basis and verification status
This page separates the supplied case narrative from independently accessible medical literature. That distinction is important: a case description can illustrate a clinical problem, but it cannot establish incidence, prove causation or demonstrate that one implant design prevents future failure.
| Information type | Source used on this page | Required verification |
| Case history and timeline | Case materials supplied to the publisher | Confirm against de-identified clinical records before publication |
| Radiographic images | Two images supplied with the original article | Confirm patient consent, ownership, de-identification and image-use permission |
| General clinical background | Peer-reviewed case reports listed below | Readers should review the original publications and their limitations |
| Product information | XC Medico product information | Verify specifications against current labeling and technical documentation |
Reported case presentation
Reported case dataThe supplied narrative describes an adult male in his early fifties with a history of posterior thoracolumbar deformity correction and fusion from T11 to L3 approximately 15 years earlier. Relevant reported factors included smoking, controlled hypertension and reduced bone mineral density.
The patient reportedly developed sharp left-sided chest pain radiating toward the scapular region, worsened by deep inspiration, together with mild exertional dyspnea over several weeks. No new lower-extremity neurological deficit was reported.
Reported clinical timeline
| Stage | Reported event | Clinical relevance |
| Remote history | Posterior thoracolumbar fusion and instrumentation | Establishes a potential late hardware-related differential diagnosis |
| Presentation | Pleuritic chest discomfort and mild exertional dyspnea | Symptoms prompted evaluation for cardiopulmonary and hardware-related causes |
| Initial imaging | Chest radiograph followed by thoracic CT | Defined the position and trajectory of the migrated hardware |
| Intervention | Reported posterior retrieval and construct revision | Aimed to remove the migrated component and address the remaining construct |
| Follow-up | Clinical and radiographic review through three months | Short-term outcome only; it does not establish long-term durability |
Imaging findings
Authorization requiredThe images below are retained from the supplied article for editorial review. They should remain public only if the publisher holds documented consent and image-use permission and has verified that they belong to the case described.
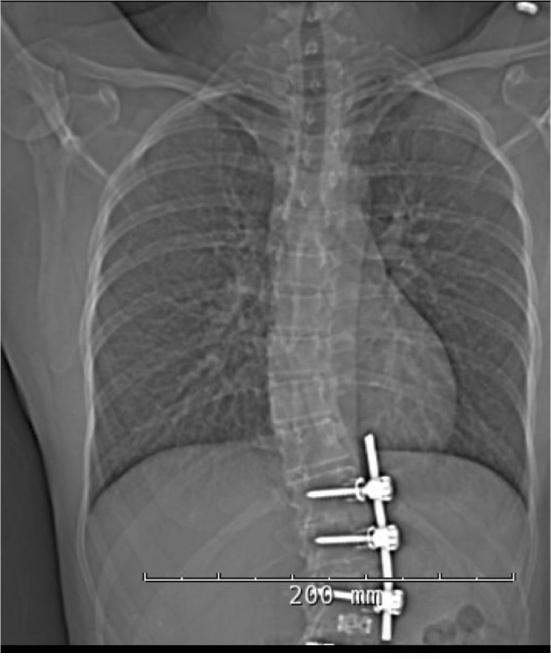
![Reported radiograph showing cephalad migration of a spinal rod toward the thoracic cavity]()
Figure 1. Supplied radiographic image reported to show cephalad displacement of a longitudinal spinal rod toward the thoracic field. Image origin, patient consent and publication permission must be confirmed before use.
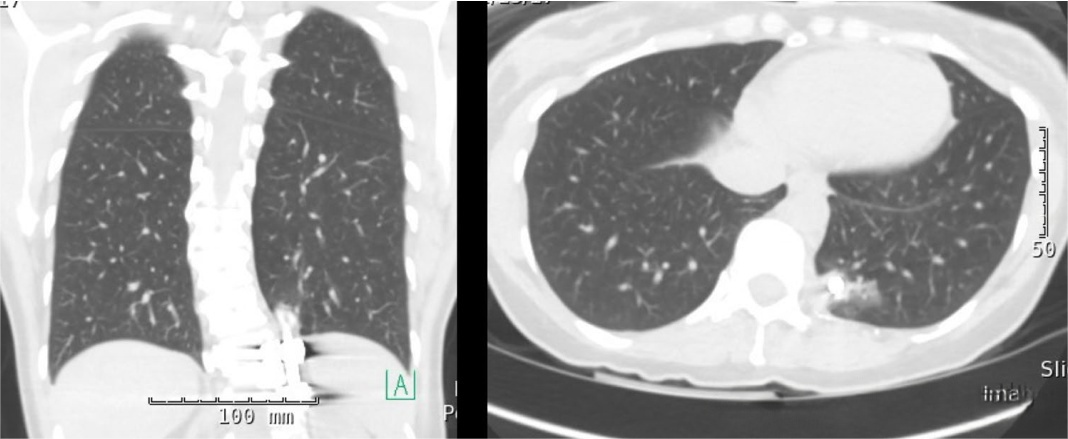
![Reported CT views used to assess the position of migrated spinal hardware near thoracic structures]()
Figure 2. Supplied CT views reported to demonstrate the position of the migrated hardware relative to thoracic structures. The final caption should be approved by the contributing radiologist or treating clinical team.
According to the supplied interpretation, the rod had disengaged from the left side of the posterior construct and migrated superiorly. CT was reportedly used to evaluate the relationship between the hardware and the pleura, lung and nearby vascular structures. Exact anatomic relationships should be described only by a qualified clinician who has reviewed the original imaging series.
Management considerations
Published cases show that management is highly case-specific. Factors that may influence planning include symptoms, fusion status, evidence of infection or nonunion, hardware integrity, bone quality, the migration tract and proximity to neural, vascular or visceral structures.
Potential approaches considered in the supplied narrative
- Targeted removal of the migrated component: may address the immediate hardware threat but does not automatically resolve instability or failure elsewhere in the construct.
- Combined anterior or thoracic and posterior treatment: may be considered when direct visualization of thoracic structures is necessary, but procedural requirements depend on the individual anatomy and multidisciplinary assessment.
- Posterior retrieval with construct revision: was the approach reported in the supplied case. Its suitability cannot be generalized to other migration patterns.
Rod migration near the thoracic cavity may create risk to pleural, pulmonary or vascular structures, but the urgency and operative route must be determined by the treating specialists. This page is not a surgical technique guide.
Reported intervention
Reported case dataThe supplied operative narrative states that the previous posterior approach was reopened, the remaining hardware was exposed, and the migrated rod was withdrawn along its existing tract under imaging guidance. The original construct was then revised using posterior pedicle screws, rods and cross-connectors.
The supplied record reports a total operative time of 155 minutes and estimated blood loss of 210 mL. These figures should be retained only if confirmed against the de-identified operative record. They describe this reported procedure only and should not be presented as expected outcomes for similar cases.
The source article referred to a reduction polyaxial pedicle screw system. Readers seeking non-clinical product details can review the reduction pedicle screw system. Product specifications must be verified against current technical documentation, and this link does not establish that the product caused the reported outcome.
Reported postoperative course and follow-up
The supplied case narrative reports improvement in chest pain after the procedure, preserved lower-extremity neurological function and mobilization during the early postoperative period. It also reports maintained construct alignment and improvement in symptoms at a three-month review.
These are short-term, case-specific observations. Phrases such as “zero micro-motion,” “perfect structural hold” or “failure eliminated” have been intentionally removed because routine follow-up imaging cannot support those absolute conclusions.
Possible mechanisms of spinal rod migration
The exact cause in this supplied case has not been independently established. Published reports discuss multiple possible contributors, including rod or set-screw disengagement, component breakage, pseudarthrosis, inadequate tightening, construct imbalance, repetitive loading, reduced bone quality and failure of fusion.
For example, published cases describe rod migration into the thoracic subarachnoid space, retroperitoneum, pelvis and pulmonary structures. These reports consistently characterize distant migration as rare and emphasize imaging and long-term follow-up rather than assigning one universal mechanism.
Do not infer a single cause
Set-screw position alone does not prove why a construct failed. Fusion status, component integrity, surgical technique and patient factors also require review.
Avoid absolute design claims
Thread geometry and cross-connectors may influence construct mechanics, but a single case cannot prove that a feature eliminates loosening or migration.
Use long-term surveillance
Some published migrations occurred years after the index procedure, supporting continued attention to new pain, neurological symptoms or unexplained cardiopulmonary complaints.
Match management to anatomy
The location of the migrated hardware relative to neural, vascular and visceral structures can materially change operative planning.
General descriptions of open spinal stabilization systems and spine implant options may help distributors understand system components. They are commercial and educational resources, not comparative clinical evidence and not proof that a particular configuration is appropriate for an individual patient.
Limitations of this case review
- The case-specific source records have not been supplied to or independently audited in this SEO review.
- Written consent, image ownership and institutional authorization must be confirmed before publication.
- This is a single reported case without a control group.
- Follow-up is limited to the period reported in the supplied narrative.
- The case cannot establish incidence, causation, device superiority or long-term failure prevention.
- Product involvement and specifications must be confirmed against traceable records and current technical documentation.
- No cost-effectiveness conclusion is made because the original cost model was inconsistent and not externally sourced.
Key learning points
- Distant spinal rod migration is rare but may involve neural, vascular, pleural or visceral structures.
- New chest, abdominal, pelvic or neurological symptoms in a patient with remote spinal instrumentation can justify evaluation for a delayed hardware complication.
- Radiography and CT can help define hardware position and support multidisciplinary planning.
- Management should consider both the migrated component and the condition of the remaining construct.
- A single favorable outcome does not prove that a product feature prevents future construct failure.
Frequently asked questions
Can a spinal rod migrate years after fusion surgery?
Published case reports document delayed rod migration several years after spinal instrumentation. It is considered uncommon, and the mechanism differs between cases.
What symptoms may be associated with migrated spinal hardware?
Symptoms depend on the migration site and may include localized pain, neurological change, respiratory symptoms or symptoms caused by irritation of nearby structures. Similar symptoms have many other causes and require clinical evaluation.
Does a cross-link prevent spinal rod migration?
Cross-links may alter construct mechanics and rotational stability in selected configurations, but they cannot be said to eliminate migration risk. Their use is determined by the treating surgeon and the requirements of the construct.
Does this case prove that one pedicle screw system is safer?
No. A single case cannot establish comparative safety or effectiveness. Those conclusions require appropriate mechanical, regulatory and clinical evidence.
Explore additional clinical case studies from XC Medico. Each case should be interpreted within its stated evidence, authorization status and limitations.
Request technical product documentation
For distributor or professional inquiries, request current specifications, labeling and technical documentation for the relevant spinal system. Product information does not replace clinical judgment or market-specific regulatory review.
Contact XC Medico Professional-use notice: This case review is for educational and business-to-business information. It is not medical advice, a surgical recommendation or evidence that any specific device will prevent hardware migration. Treatment decisions must be made by qualified clinicians using patient-specific information and applicable product labeling.